VBAC success rates land somewhere between 60% and 80% for most people who attempt a vaginal birth after cesarean, sit around 70% to 75% after a single previous cesarean, and fall to roughly 50% after two or more. The strongest single predictor is whether you have already had a vaginal birth, before or after your cesarean.
Those are group averages, not a forecast for your body. This guide walks through how the numbers are calculated, which factors push them up or down, why two hospitals can quote 55% and 82% for the same person, and what to do with the percentage your provider or an online calculator gives you.
This is educational information about population-level outcomes, written with reference to ACOG Practice Bulletin 205, the 2025 FIGO good practice recommendations, and named cohort studies. It is not a substitute for advice from your own obstetric clinician, and the only person who can estimate your individual odds is the provider who has your records.
Read the ACOG patient FAQ on vaginal birth after cesarean alongside this guide so you can match the numbers here to the guidance your clinician is working from.
Table of Contents
- What Is a VBAC and How Are Success Rates Measured?
- What Is the Typical VBAC Success Rate?
- What Factors Most Affect VBAC Success Rates?
- Absolute contraindications versus relative risk factors
- What raises and lowers your odds: the short version
- How Does the Reason for the First Cesarean Matter?
- How Do Age, Weight, Medical Conditions, and Induction Affect the Odds?
- What Do Hospital and Provider Practices Mean for VBAC?
- How Can Someone Prepare for a VBAC?
- Frequently Asked Questions
- What are the most common reasons a VBAC is not successful?
- What increases the chance of a successful VBAC?
- What percentage of VBACs end in another cesarean?
- What actually disqualifies someone from a VBAC?
- Is induction risky for a VBAC?
- What happens to your chances after two previous cesareans?
- What Should You Do First?
What Is a VBAC and How Are Success Rates Measured?
A VBAC is a vaginal birth after cesarean. It is the delivery itself. What gets quoted as a success rate is usually one step earlier in the process, which is why the terminology confuses so many readers.
- TOLAC (trial of labor after cesarean): the plan to attempt vaginal birth after a previous cesarean. You can have a TOLAC and still end up with a cesarean.
- VBAC: a successful vaginal birth following a cesarean. This is the outcome the percentage describes.
- CBAC (cesarean birth after cesarean): labor started, then ended in another cesarean. Clinicians use the term; many people who have been through it dislike it.
- ERCS (elective repeat cesarean, also written repeat cesarean birth): a planned cesarean without labor.
So when a hospital says its VBAC success rate is 70%, it usually means 70% of people who attempted labor after their prior cesarean went home with a vaginal birth. A quarter to a third of the remainder had a cesarean after labor began.
That distinction sets up the single most important framing rule in this whole subject: the meaningful comparison is planning a TOLAC against planning an ERCS, never a successful VBAC against a cesarean. You cannot skip labor and go straight to the good outcome. Choosing to attempt a VBAC means accepting both possible endings in the same package, which is how ACOG frames it and how Evidence Based Birth explains it.
Success rate is measured as a proportion, usually from hospital or population cohort data such as the Landon 2004 trial of labor after cesarean study published in the New England Journal of Medicine, or the Guise 2010 AHRQ evidence review. Individual percentages come from prediction models that weight the predictors listed below, most commonly the Grobman 2007 prenatally applied nomogram, the Metz 2013 admission-time model, or the Fagerberg and Kallen 2019 Swedish third-trimester model.
What Is the Typical VBAC Success Rate?
Roughly 60% to 80% is the range the FIGO 2025 good practice recommendations, ACOG Practice Bulletin 205, and most consumer health pages agree on. After one prior cesarean, cohort data cluster around 70% to 75%. After two or more, published rates drop toward 50%.
The wider spread matters more than the headline. Australia’s Safer Care Victoria states plainly that planned VBAC success ranges from 29% to 82% depending on the population, which is not an error. It reflects who was offered a trial, how labor was managed, and which hospital.
| Group or setting | Reported VBAC success rate | How to read it |
|---|---|---|
| General population, one previous cesarean | About 60% to 80% | The headline range; a bundle of very different people |
| After one prior cesarean, cohort averages | About 70% to 75% | The number most often quoted to a first-time VBAC candidate |
| After two or more prior cesareans | About 50% | Roughly a coin flip; many hospitals still offer a TOLAC |
| People who have previously had a vaginal birth | Often 80% and above | Prior vaginal delivery is the strongest single predictor |
| Labor induced rather than spontaneous | Lower than spontaneous onset | Method matters: induction agent changes the numbers |
| Hospital-level published rates | 29% to 82% | Safer Care Victoria range; reflects case mix and policy |
Now the number you will actually be given. Many providers and most online calculators produce something like 55% or 91% for the same person. That gap is not a mystery once you know what is inside the calculation, which we come to later in this guide.
What Factors Most Affect VBAC Success Rates?
The factors that raise your odds most are a previous vaginal birth, spontaneous onset of labor, a low transverse uterine scar, a reason for the first cesarean that has not recurred, no other uterine surgery such as a myomectomy, and giving birth in a facility with immediate surgical capability. The factors that pull the number down are induction, a prior cesarean for labor arrest or a failed induction, a larger estimated fetal weight, maternal age over 35, a BMI of 30 or higher, a short interval since the last birth, and a preeclampsia diagnosis in the current pregnancy.
| Factor | Effect on odds | Rough magnitude | Source |
|---|---|---|---|
| Previous vaginal birth (before or after the cesarean) | Raises | Strongest single predictor; pushes rates toward 80% and above | Evidence Based Birth, 2020; Grobman 2007 |
| Spontaneous onset of labor | Raises | Induced labor succeeds less often than spontaneous labor | Landon 2004; Guise 2010 |
| Low transverse uterine scar | Raises | Rupture risk roughly 0.4% to 0.9% during labor | ACOG Practice Bulletin 205 |
| Non-recurring prior indication, such as fetal heart rate decelerations | Raises | Substantially higher than after labor arrest | PMC systematic review, 2023; FIGO 2025 |
| No prior myomectomy or other uterine surgery | Raises | Removes an independent rupture contributor | Cleveland Clinic, 2024 |
| Maternal age 35 and over | Lowers | Cohorts commonly show success in the 60s rather than the 70s | Landon 2004; Grobman 2007 |
| BMI of 30 or higher | Lowers | Low-to-mid 60s versus low 70s below 30 | Landon 2004 |
| Estimated fetal weight above 4000 g | Lowers | Adds to shoulder dystocia and failed-push concerns | Cleveland Clinic, 2024 |
| Interval under 18 months since last cesarean | Lowers | ACOG suggests waiting at least 18 months, many prefer 24 | ACOG Practice Bulletin 205; Mayo Clinic 2025 |
| Two or more prior cesareans | Lowers | About 50% on average | Guise 2010; Cleveland Clinic 2024 |
| Induction, agent-dependent | Lowers | Rupture roughly 1.1% with Pitocin, 2% with prostaglandins, 6% with misoprostol | Evidence Based Birth, 2020 |
| Birth in a facility without immediate surgical capability | Lowers or removes the option | Institutional, not personal; many such units decline a TOLAC outright | FIGO 2025; ACOG 205 |
Absolute contraindications versus relative risk factors
Most reader confusion comes from treating every risk factor as disqualifying. A small number of situations make a trial of labor inadvisable, and many more simply lower the expected success rate while leaving the option open.
Generally considered reasons not to plan a TOLAC: a prior classical or inverted T uterine incision, a previous uterine rupture, a known uterine anomaly that would distort the scar, placenta previa or vasa previa in the current pregnancy, active herpes with active lesions at the time of labor, or a current pregnancy where cesarean delivery is required for a non-obstetric reason. Prior low vertical incisions sit in a contested middle ground, and guidelines differ on how they are handled.
Relative risk factors, which change the number rather than closing the door: age over 35, elevated BMI, estimated fetal weight above 4000 g, induction, gestational hypertension or preeclampsia, diabetes, post-term pregnancy, a short birth interval, and more than one previous cesarean.
Ask directly which category your provider is placing you in. A risk factor treated as a hard stop at one hospital is often treated as a discussion point at the next one.
What raises and lowers your odds: the short version
Readers ask for two lists more than anything else, so here they are without the table. Raising the odds: a previous vaginal birth, labor that starts on its own, a low transverse scar, a non-recurring prior reason for the cesarean, no other uterine surgery, a singleton cephalic fetus at an estimated weight under 4000 g, an interval of 24 months or more, a healthy BMI, and a hospital with 24/7 anesthesia and surgical capability.
Lowering the odds: induction, especially prostaglandins or misoprostol, a prior cesarean for labor dystocia or failed induction, multiple prior cesareans, estimated fetal weight above 4000 g, maternal age over 35, obesity, preeclampsia, a post-term due date, and an interval under 18 months.
How Does the Reason for the First Cesarean Matter?
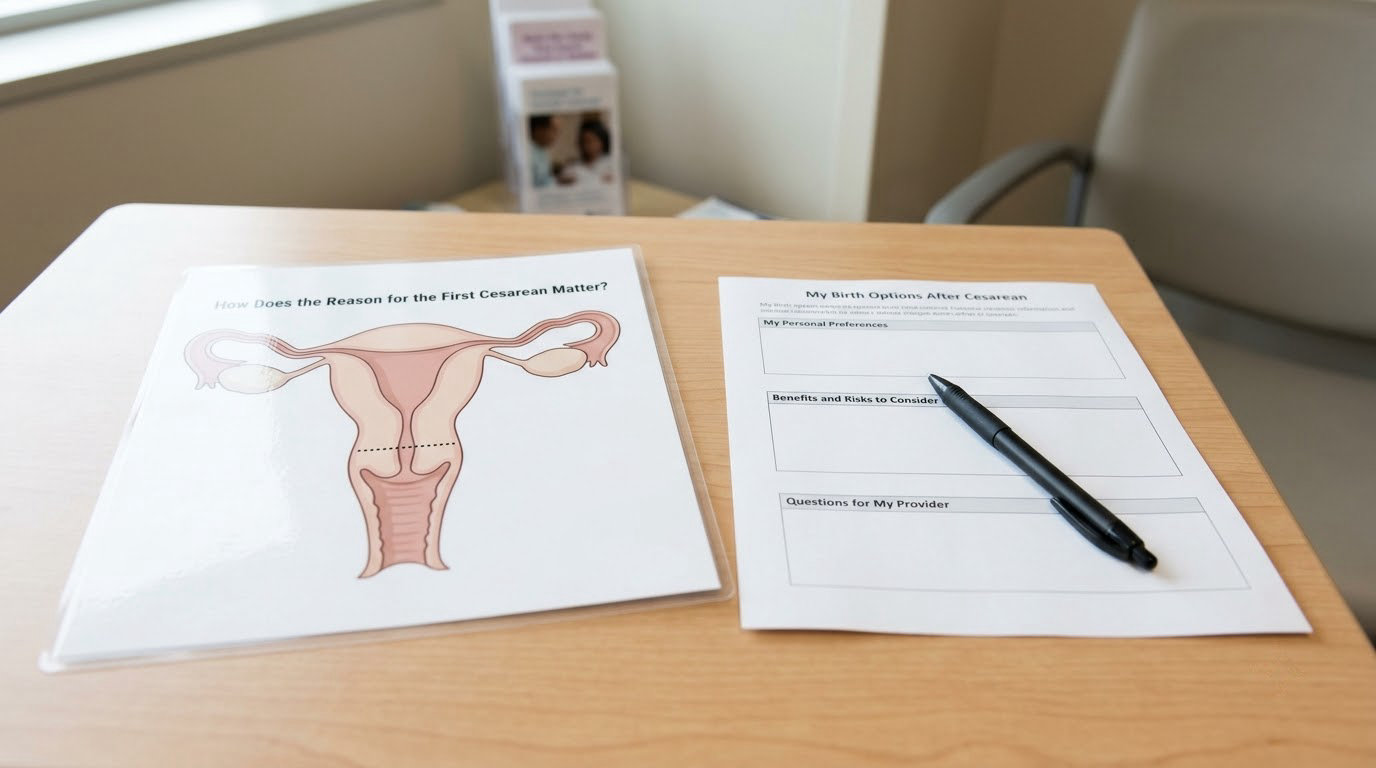
The indication for your first cesarean is one of the strongest predictors of whether the second birth will be vaginal, because it tells your clinician whether the same problem is likely to happen again. A cesarean for fetal heart rate decelerations describes a circumstance that may not recur. A cesarean for a pelvis that never opened describes a mechanical fact that will still be there.
| Reason for the prior cesarean | Effect on VBAC outlook | Why |
|---|---|---|
| Fetal heart rate abnormalities or other non-recurring indication | Favorable | The reason was a moment in labor, not a lasting feature |
| Placenta previa, abruption, cord prolapse | Favorable for the birth itself | Often situational; note that previa may recur |
| Breech or other malpresentation | Mixed | The position may repeat, so this birth needs confirmation of presentation |
| Labor arrest or poor progress (dystocia) | Less favorable | Pelvic and tissue factors may persist; cited success often falls into the 60s, and lower estimates appear in some cohorts |
| Failed induction | Least favorable of the common indications | Questions whether the uterus and cervix respond to labor at all |
| Medical indication such as cardiac or seizure disorder | Depends entirely on the condition | Requires individual obstetric and medical assessment |
Two things are worth correcting here, because both come up constantly. First, the abdominal scar and the uterine scar are not the same thing, and one does not reliably tell you where the other is. Only the operative report does.
Second, a cesarean for failure to progress is frequently treated as near-disqualifying. The evidence is softer than that framing suggests. A 2023 systematic review in PMC reports overall success above 60% even where the prior cesarean was for poor labor progress, and other cohort data place it in the 60% to 65% range. Where you will see much lower figures, such as 20% to 40%, is in cohorts dominated by a prior failed induction, which is a genuinely different situation.
On Reddit’s r/vbac, birthing people with a prior cesarean for failure to progress describe being quoted figures as low as 20% with no explanation of the inputs. That is worth challenging in the room, because it is not what the cohort literature consistently shows.
How Do Age, Weight, Medical Conditions, and Induction Affect the Odds?

Age, weight, medical conditions and induction all shift the expected success rate, and every one of them also changes how your labor would be managed. That second effect is often the larger one in practice.
Age. Maternal age over 35 lowers success into the 60s in most cohort data, and also raises the rate of interventions such as induction. Age 40 and over is a bigger shift still. It is a risk modifier, not a contraindication, and plenty of people over 35 have uneventful VBACs.
Weight. A BMI of 30 or above is associated with success in the low-to-mid 60s. Above 40, most guidelines recommend cesarean delivery. Higher BMI also changes anesthesia access and surgical timing, which affects how comfortable a TOLAC feels for everyone involved.
Medical conditions. Gestational hypertension, preeclampsia, diabetes, and a post-term due date each reduce expected success. Preeclampsia in particular changes the delivery timing decision entirely, and often removes the option of waiting for spontaneous labor.
Fetal size. An estimated fetal weight above 4000 g is the usual threshold that appears in guidelines, though some use 4500 g with diabetes as a co-factor.
Induction. This is where the most decision-relevant numbers live, and where different agents differ sharply in rupture risk.
| How labor starts | Effect on success | Rupture risk during TOLAC |
|---|---|---|
| Spontaneously | Highest | About 0.4% to 0.9% with a low transverse scar |
| Induced with intravenous Pitocin (oxytocin) | Lower than spontaneous | About 1.1% |
| Induced with a prostaglandin | Lower | About 2% |
| Induced with misoprostol | Lowest, and generally avoided in a scarred uterus | About 6% |
Those rupture figures were compiled by Evidence Based Birth in 2020 from cohort studies, and they are the numbers most consumers have never seen. The practical takeaway is that the choice of induction agent matters more than the general fact of induction, and that misoprostol is the one most guidelines say to avoid in a scarred uterus.
Induction also shortens the window. A TOLAC that stalls at six centimeters after eight hours of oxytocin is a different situation from a TOLAC that has been in spontaneous labor for twelve hours, and definitions of adequate trial vary between hospitals. Ask yours how it defines an adequate trial of labor for a VBAC before you are in one.
What Do Hospital and Provider Practices Mean for VBAC?
The number you get is partly a property of the place you gave birth in, not only of your body. This is the part of the topic that mainstream patient pages rarely explain, and it explains most of the confusion in the numbers.
Case mix. A hospital that only offers a TOLAC to people with a prior vaginal birth will publish a very high success rate. A hospital that offers it to everyone with a low transverse scar will publish a lower one. Neither hospital is doing anything wrong.
Selection effects and the self-fulfilling prophecy. If a provider tells you your chance is 55%, and labor is then managed to that number, the prediction becomes the cause. People on r/vbac describe exactly this: a low estimate stated out loud, followed by less patience with early labor. Evidence Based Birth makes the same point about calculators, which were never validated to reduce complications and do not account for a person’s values or the practice setting.
Institutional policy. US VBAC rates fell from about 28% in 1998 to 9.2% in 2004, driven by a 1985 ACOG statement, a 1999 requirement that anesthesia be immediately available, and malpractice concerns. By 2009 roughly 30% of US hospitals had a formal ban. Many bans have since softened, and a de facto ban looks identical to a real one from the outside.
Equity. Race enters some VBAC prediction models, and lower measured success rates among Black, Asian and Latina birthing people in the United States reflect systemic factors: access to continuity of care, differences in hospital resources, de facto bias in who is offered a TOLAC, and bias in how labor is managed once a prediction exists. Evidence Based Birth documents this carefully. Lower measured rates are not a biological fact about a group, and an individual number should never be read as one.
The balance on the other side. Every repeat cesarean adds surgical risk. Placenta accreta risk climbs with each cesarean, per Silver and colleagues in 2006: about 0.31% at a second birth, 0.57% at a third, 2.13% at a fourth, 2.33% at a fifth and 6.74% at a sixth. Adhesions, blood loss, and the slower recovery that follows from operating on a scarred uterus all belong in the same conversation, which is why planned family size is a legitimate input into the decision.
Guidelines. Four documents shape practice today, and they do not agree on every point.
| Guideline | Where it stands |
|---|---|
| ACOG Practice Bulletin 205 (2019, reaffirmed 2024) | Most TOLACs are appropriate; VBAC is a reasonable option; prior classical incision, prior rupture and certain other situations are contraindications |
| FIGO good practice recommendations (2025) | Success 60% to 80%; supports a supportive institutional environment; emphasizes that most candidates are suitable |
| RCOG Green-top Guideline No. 45 | More selective; discusses one previous cesarean as the main group and multiple prior cesareans more cautiously |
| NICE NG192 | Advises discussing individualized factors and emphasizes counseling and birth-center eligibility questions |
If you are told a VBAC is not available to you, ask which guideline the hospital is applying and whether it has a written policy. Often the answer is a local policy that predates current ACOG guidance.
How Can Someone Prepare for a VBAC?
Preparation is mostly about getting the right information into the room before labor starts, not about anything physical you can do to your uterus.
Get your operative report. This is step one and everything else depends on it. Contact the hospital’s medical records department and request the operative note from your cesarean, or ask your surgeon’s office. You are looking for the name of the uterine incision: low transverse, low vertical, classical, or inverted T. Only the report will tell you. Patients on r/vbac describe this as the hardest practical step in the whole process, and it is usually solvable with a records request and a few weeks of patience.
Ask for the inputs behind the number, not just the number. If you were given 55%, ask which factors went into it and which model was used. A number with no stated basis is an opinion formatted like a calculation.
Ask how the hospital handles labor. Continuous fetal monitoring, whether an epidural is required, how long they will support a slow labor, whether they define an adequate trial differently for a VBAC, and who is called when you arrive. These are the operational details that determine the outcome.
Arrange support. A doula or a dedicated partner is one of the few factors on the raise-your-odds list that you fully control. People describe continuous support as the difference between a long labor and a long labor that ends in a cesarean at four centimeters.
Prepare for both endings. Make the plan for a cesarean as concrete as the plan for a vaginal birth, including who cares for your older child, how you will get your birth record for your next pregnancy, and what a repeat cesarean recovery actually involves. On this point be honest with yourself: a CBAC, meaning a cesarean after labor has begun, carries more morbidity than either a planned VBAC or a planned repeat cesarean, because you have had the exposures of both. Knowing that in advance is not defeatism. It is the comparison you actually signed up for.
Consider a second opinion. If a consultation produced a discouraging number, an independent second opinion from a midwife or an obstetrician at a different institution is a reasonable step, and it is a normal one to take.
Frequently Asked Questions
What are the most common reasons a VBAC is not successful?
Most unsuccessful VBACs happen because labor does not progress adequately, particularly after induction with oxytocin, or because the pelvis and soft tissues that caused the first cesarean present the same obstacle again. Uterine rupture accounts for a very small fraction. The rest are planned or unplanned cesareans for fetal heart rate concerns, malpresentation, or a changed clinical picture such as preeclampsia. In most cohorts, poor progress in labor makes up the majority of cases.
What increases the chance of a successful VBAC?
The strongest predictor is having previously had a vaginal birth, whether it came before or after your cesarean. After that come spontaneous onset of labor, a low transverse uterine scar, a reason for the first cesarean that has not recurred, no other uterine surgery such as a myomectomy, a singleton baby in a head-down position with an estimated weight under 4000 grams, and giving birth in a unit with immediate surgical and anesthesia capability.
What percentage of VBACs end in another cesarean?
If overall VBAC success runs from 60% to 80%, then between 20% and 40% of planned VBACs end in a cesarean after labor begins. The figure depends heavily on induction use: hospitals with low induction rates report fewer CBACs. After one previous cesarean the unsuccessful group is usually around 25% to 30%, rising to roughly half after two or more prior cesareans.
What actually disqualifies someone from a VBAC?
A prior classical or inverted T uterine incision, a previous uterine rupture, an unexplained uterine anomaly, placenta previa in the current pregnancy, active genital herpes lesions at the time of labor, or a condition requiring cesarean delivery regardless of route. Age over 35, an elevated BMI, a large estimated fetal weight, induction, preeclampsia and a short birth interval are risk modifiers that change the expected success rate without closing the option.
Is induction risky for a VBAC?
Induction lowers both the chance of success and the margin for error, and the agent matters. Compiled cohort figures put rupture risk at about 1.1% with intravenous oxytocin, about 2% with prostaglandins and about 6% with misoprostol in a TOLAC, compared with roughly 0.4% to 0.9% for spontaneous labor after a low transverse scar. That is why many guidelines advise against misoprostol in a scarred uterus.
What happens to your chances after two previous cesareans?
After two or more prior cesareans, published success rates cluster near 50%, compared with 70% to 75% after one. The reduction reflects both the accumulated surgical scar and the fact that people with repeated cesareans more often had early cesareans for indications that can recur. Having a prior vaginal birth still raises the number substantially. Many hospitals will plan a TOLAC after two cesareans; some will only offer a third in a trial of labor.
For reference, the studies and guidelines cited here are ACOG Practice Bulletin 205 (2019, reaffirmed 2024), FIGO good practice recommendations for vaginal birth after cesarean delivery (2025), Landon and colleagues (2004, New England Journal of Medicine), Guise and colleagues (2010, AHRQ Evidence Report 191), Silver and colleagues (2006), Grobman and colleagues (2007), Metz and colleagues (2013), Fagerberg and Kallen (2019), Safer Care Victoria birth after caesarean guidance, and Evidence Based Birth episode 113 (2020). Guidance changes, so check the current version of each with your care team. This article was last reviewed in 2026 and is educational only.
What Should You Do First?
Request your operative report from your previous cesarean and read the uterine incision type. That single document changes the conversation more than any percentage you will be quoted, because scar location determines both the safety profile and which guidelines apply.
Then take that report, plus your current pregnancy records, to an obstetric clinician and ask two things: which factors went into my estimated success rate, and which of my risk factors are being treated as contraindications rather than modifiers. Use the population statistics in this guide as context for that conversation, not as a prediction of your own outcome.
If the number you were given sits far outside the 60% to 80% band and nobody explained how it was derived, ask for the inputs or seek a second opinion. An unexplained percentage is the most common and least deserved obstacle people face on this path.