If you have heard the word “induction” mentioned at a prenatal visit, the first thing you want is a straight answer about why it came up at all. The reasons doctors recommend inducing labor are almost always one of the same handful: a time-sensitive concern about your health or your baby’s health, a pregnancy that has run past the due date, or a practical situation that makes waiting harder. It is worth knowing that induction is common, that it is usually offered as a shared decision rather than a directive, and that you are allowed to ask exactly what risk it is meant to reduce.
This guide walks through each of those reasons in plain language, explains how clinicians weigh the risks of delivering now against the risks of waiting, and finishes with the questions worth asking at your next appointment. Nothing here replaces advice from the clinician who knows your chart.
Table of Contents
- What Is Labor Induction?
- Reasons Doctors Recommend Inducing Labor
- How Do Doctors Decide Whether Induction Is Necessary?
- What Medical Conditions Can Lead to Induction?
- Why Might Induction Be Suggested After the Due Date?
- Can Induction Be Recommended for a Healthy Pregnancy?
- How Is Induction Different From Starting Labor With Medication?
- What Happens During an Induction Consultation?
- What Are the Benefits and Risks of Induction?
- What Questions Should You Ask Before Induction?
- Frequently Asked Questions
- Is induction recommended only when there is a medical problem?
- Does induction mean I am choosing a cesarean birth?
- Can I decline an induction if I have no medical reason for it?
- What happens if an induction does not work?
- Is walking or changing position an alternative to hospital induction?
- When should I contact my doctor urgently instead of waiting for a scheduled induction?
- What to Do First
What Is Labor Induction?
Labor induction is the process of starting or speeding up labor before it begins on its own. Your care team uses medications, mechanical devices, or breaking your water to soften and open the cervix and then bring on contractions.
Two different jobs sit inside the word “induction.” Cervical ripening comes first, and it means softening, thinning, and slightly opening the cervix so it can begin to change. Augmentation comes second, and it means strengthening contractions that are already happening but are not strong enough or close enough together.
That distinction matters in conversation. If a provider mentions ripening, the goal may still be several hours away from birth, and it can take a full day before anything changes.
Reasons Doctors Recommend Inducing Labor
Induction gets recommended for a fairly short list of underlying reasons, even though it is phrased differently in every clinic. Knowing which category yours falls into tells you a great deal about how urgent it is and how much room you have for discussion.
- A medical condition affecting you — high blood pressure, preeclampsia, diabetes, or a heart, kidney, or blood problem that becomes harder to manage as pregnancy continues.
- A medical condition affecting your baby — the baby measuring small or large, reduced movement, a heart rate pattern that needs watching, or an ultrasound finding that concerns the team.
- Low amniotic fluid (oligohydramnios) — fluid that is low enough to limit growth or cushioning.
- Your water broke before labor started (premature rupture of membranes, or PROM) — a time-limited situation because infection risk rises once membranes are open.
- An infection in the uterus (intrauterine infection, sometimes called chorioamnionitis) — usually with fever or a fast heartbeat.
- Pregnancy past the due date (post-term pregnancy) — commonly discussed at 41 weeks and beyond, sometimes earlier for a specific reason.
- A previous pregnancy that ended in stillbirth — many plans offer earlier delivery after a loss, guided by your own history.
- Practical circumstances that make waiting difficult — living far from the hospital, no support person available, or a provider who will not be able to attend a later birth. These are legitimate considerations, but they are not the same as a medical emergency.
Two things are worth saying plainly. In many births, there is no single dramatic condition; the reason is a mix of a couple of low-grade concerns plus how close you are to the due date. And the more serious the indication, the less of a decision it is.
How Do Doctors Decide Whether Induction Is Necessary?
It is a comparison, not a checklist. A clinician looks at how far along you are, how ready your cervix is, how the baby is positioned, your overall health, recent test results, and your obstetric history — then asks whether the expected benefit of delivering sooner clearly outweighs the risks of waiting.
Cervical readiness gets a lot of attention because it predicts how well induction will work. A cervix that is soft, thinned, and slightly open responds differently from one that is firm and closed, and it shapes both the method chosen and how long the process may take.
Most of the time the calculation points the same direction: a specific risk exists, it grows with time, and delivery resolves it. When the risk is small and slow-changing, waiting is reasonable, and a second opinion is entirely legitimate to ask for.
What Medical Conditions Can Lead to Induction?
The conditions below are the ones that most often show up in conversations about induction. Each one gets its own threshold, test, and plan, so the same diagnosis can lead to two different recommendations for two different people.
Preeclampsia and high blood pressure. New or worsening high blood pressure with signs that other organs are affected, or sometimes without them, changes the balance toward delivering. Protein in the urine, severe headache, visual changes, upper abdominal pain, or lab changes all make the timing more pressing.
Gestational diabetes or pre-existing diabetes. Blood sugar control near the end of pregnancy is the deciding factor, and induction is often scheduled so the plan is controlled rather than urgent. Being told you have gestational diabetes does not automatically set a delivery date; the numbers do.
Fetal growth restriction. When the baby measures small, the team weighs whether the placenta is still supporting well. Continued pregnancy can work, but when growth slows or the blood flow to the baby changes, delivery becomes the safer option.
Low amniotic fluid. A thin cushion of fluid means less room for the cord to be compressed during movement and contractions, and less fluid to support growth. The amount, the trend, and how you are doing all factor in.
Reduced or changed fetal movement. A pattern of noticeably quieter or smaller movement is one of the most common reasons a clinician wants to move things along, and one worth acting on quickly rather than debating.
Ruptured membranes with no contractions. Once the water breaks and labor does not start, there is a clock. The risk of infection climbs with time, which is why many plans favor starting labor within about a day rather than waiting for contractions to appear on their own.
Infection. A fever, a racing heart, or a change in the fluid’s appearance can point to an infection in the uterus. This is one of the few situations where induction is discussed as urgent rather than scheduled.
Post-term pregnancy. Once the due date passes, the risk profile of the pregnancy changes even though nothing feels different. That is the subject of the next section.
Why Might Induction Be Suggested After the Due Date?
Most due dates are estimates, and roughly half of births do not happen on the one you were given. The concern after 41 weeks is not that something is going wrong, but that the placenta is a temporary organ with a usable lifespan, and its efficiency tends to shift late in pregnancy.
Past the due date, clinicians weigh three things more closely: fluid volume, which often drops; the baby’s size, which tends to keep increasing; and the small but real increase in stillbirth risk. None of these are dramatic on a daily basis, and that is exactly why the conversation at 41 weeks is a genuine choice between continuing the pregnancy and delivering it.
Expectant management, which means monitoring and waiting, is a legitimate path for some people. It usually involves more frequent checks of fluid, movement, and the baby’s heart rate. Ask what the plan is, what would change the answer, and how quickly the team could respond if something shifted.
Can Induction Be Recommended for a Healthy Pregnancy?
Yes, but the reasoning looks different, and you are owed a clear explanation of which kind you are being offered. An induction in an uncomplicated pregnancy is typically called elective or scheduled, and it is meant to reduce specific risks such as a large baby, low fluid, or the small rise in stillbirth risk after the due date.
Elective induction before 39 weeks is generally not offered, because early delivery carries its own risks that grow the sooner it happens. An offer at 39 or 40 weeks for a low-risk pregnancy is a legitimate option to discuss, not a medical necessity.
You can ask for the benefit to be spelled out, ask what waiting looks like instead, and ask how long you can safely wait. If the answer is vague, that is a reasonable thing to press on in a follow-up conversation or with a second opinion.
How Is Induction Different From Starting Labor With Medication?
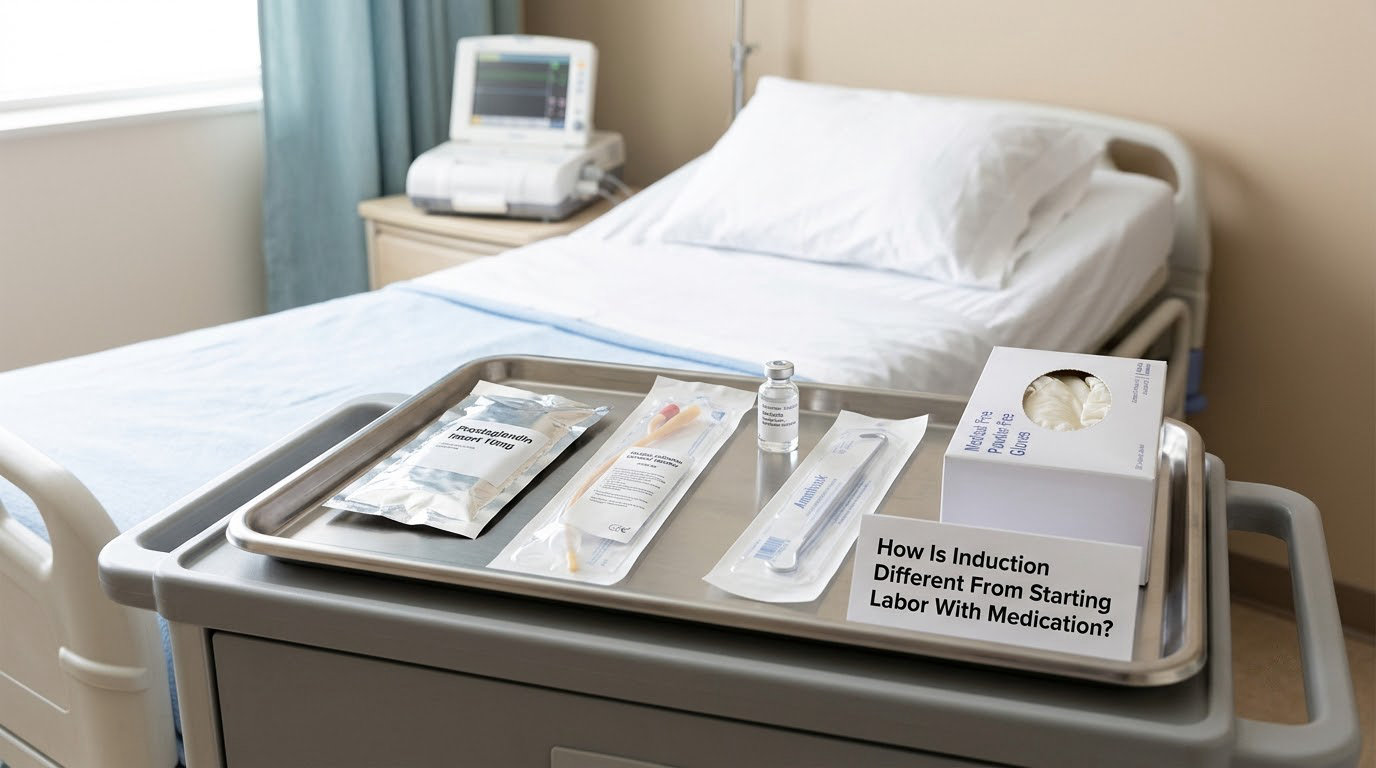
Induction happens in stages, and the methods used in each stage are different. Your provider will pick a path based on how ready your cervix is, how urgent the reason is, and what your hospital offers.
Membrane sweeping is a digital examination in which the provider separates the membranes from the lower uterus. It can bring on stronger contractions and sometimes starts labor within hours. It is uncomfortable in the moment and can cause cramping and some bleeding, which is normal but alarming if you have not been warned.
Prostaglandins are medications placed near the cervix to help it ripen. They are useful when the cervix is not ready, and they can produce cramping, backache, and sometimes a significant warm flush or chills afterward.
A balloon catheter is a small balloon placed inside the cervix for pressure. It works on the cervix mechanically rather than chemically, which some people find more tolerable, and it can stay in place for several hours.
Amniotomy, or breaking your water often encourages contractions to begin. Contractions usually get stronger faster afterward, so it is usually not done early in the process.
Oxytocin, sometimes called Pitocin is an IV medication that starts or strengthens contractions. It is adjusted over time, and because it can cause contractions that come too close together, monitoring usually continues for a while afterward.
None of this requires you to decide alone, and none of it happens without your consent. You can ask which method is planned, why it suits your situation, and what the alternatives are.
What Happens During an Induction Consultation?
An induction consultation is usually a conversation in an office or a prenatal visit, and it is often the first time the topic is named out loud. It can feel bigger than it is, so it helps to know roughly what gets covered.
Expect to hear the indication explained in terms of risk, not symptoms. Because you feel well, the reason can sound abstract; the clinician is usually talking about a probability curve, not something bad that is happening now.
Ask about the method, how long it commonly takes, how often it works the first time, what monitoring looks like, when an epidural could be available, and your hospital’s policies on support people, food, and mobile movement.
Also ask about the fallback. If labor does not start, how long will the team try before reassessing, and what options exist at that point?
What Are the Benefits and Risks of Induction?
The main benefit is resolving something time-sensitive. Delivery ends preeclampsia, removes a compromised placenta, closes the window on infection after your water breaks, and gets a baby out of a situation that is getting riskier the longer it continues.
On the other side, induced labor often takes longer than spontaneous labor and usually involves continuous or near-continuous monitoring. Contractions can come on fast and strong, and managing that relief early is sometimes harder than catching pain once it has built.
Some inductions do not work, which is called a failed induction. If the cervix has not changed enough despite the method used, the team may recommend rest and another attempt, or a cesarean, depending on the situation. For some conditions, including large babies and some types of fetal growth restriction, induction is planned partly to reduce the chance of needing a cesarean.
Rare but serious risks include a uterine tear during a contraction if there is a scar on the uterus from a prior cesarean, an abnormal heart rate pattern that requires an emergency delivery, heavy bleeding after birth, and infection. Ask how your history changes these numbers, because they are not uniform across everyone.
What Questions Should You Ask Before Induction?
Writing these down works better than trying to remember them in the room. Take the list to the appointment and let your provider answer in their own words.
- What exact reason is being given for induction, in clinical terms?
- How urgent is it? What happens if we wait one week?
- What is the specific risk you expect induction to reduce?
- What are the realistic downsides for me and my baby?
- Which method are you planning, and why that one?
- How long does this usually take, and how often does it work the first time?
- What monitoring will I have, and when can I get an epidural?
- Are there hospital limits on support people, walking, or food?
- What is the plan if labor does not progress?
- Is a second opinion reasonable before I decide?
One more question is worth saving: what would make you want to change your mind. Hearing the answer tells you how closely your provider is actually watching the situation.
Frequently Asked Questions
Is induction recommended only when there is a medical problem?
No. Clinicians may recommend induction for a time-sensitive maternal or fetal concern, after the due date, and sometimes for practical reasons such as distance from the hospital or coordinating support people. That last category is called an elective induction and should be presented as a choice with clear reasoning, not as a necessity. You can ask which category yours falls into.
Does induction mean I am choosing a cesarean birth?
Not necessarily. Induction starts or encourages labor and does not determine the delivery method. Some inductions are planned partly to reduce the chance of a cesarean, particularly when a large baby is expected. Outcomes depend on the pregnancy and how labor progresses, so ask your provider how cesarean risk applies to your situation specifically.
Can I decline an induction if I have no medical reason for it?
You can discuss alternatives and your preferences with your maternity care team. The team should explain the reason, expected benefits, risks of waiting, and what happens if you decline. When an induction is offered for convenience rather than necessity, it is reasonable to ask for more time. If a time-sensitive concern is involved, ask what specific risk it addresses before deciding.
What happens if an induction does not work?
The clinician may reassess cervical progress, fetal position, contractions, and signs of complications. Depending on the situation they may rest and try a different method, continue with augmentation, or recommend a cesarean. Failed induction is uncommon, and the honest question to ask up front is how the team would handle it and what would trigger that decision.
Is walking or changing position an alternative to hospital induction?
Movement and position changes can help with comfort and may support early labor, but they do not resolve conditions such as preeclampsia, low amniotic fluid, a growth-restricted baby, or an infection. Walking also cannot restart labor reliably. If you want to try natural methods first, ask how long that can safely be tried and what would end the attempt.
When should I contact my doctor urgently instead of waiting for a scheduled induction?
Seek prompt medical advice for reduced or changed fetal movement, severe headache, visual changes, upper abdominal pain, sudden swelling, fever, leaking fluid with a change in its colour, vaginal bleeding, or regular painful contractions before your planned date. These can signal a time-sensitive problem that should not wait for a scheduled appointment. Use your local urgent maternity service or emergency department.
What to Do First
Start by asking your obstetrician, midwife, or maternity care team one question: what specific risk is this induction meant to reduce, and what happens if we wait. That single answer usually tells you whether you are dealing with a time-sensitive concern or a preference you have room to discuss.
Write down what you hear, including the words your provider uses, because matching those terms to your chart later is genuinely useful. If the explanation feels thin, ask for a second opinion. That is a routine request, not an insult.
And do not wait on the worrying signs. Reduced or changed movement, severe headache, visual changes, upper abdominal pain, fever, bleeding, or fluid leaking with a change in colour deserve a phone call today, not a scheduled appointment. This guide is general information about why clinicians recommend induction, and your own plan should come from the person who knows your pregnancy.